
Low-Dose Naltrexone for Fibromyalgia
… How to Give LDN a Fair Trial
Home | Treatment & Research News

Is LDN worth trying when standard fibromyalgia drugs often disappoint or cause side effects? That is the question many patients ask when they hear about low-dose naltrexone for fibromyalgia.
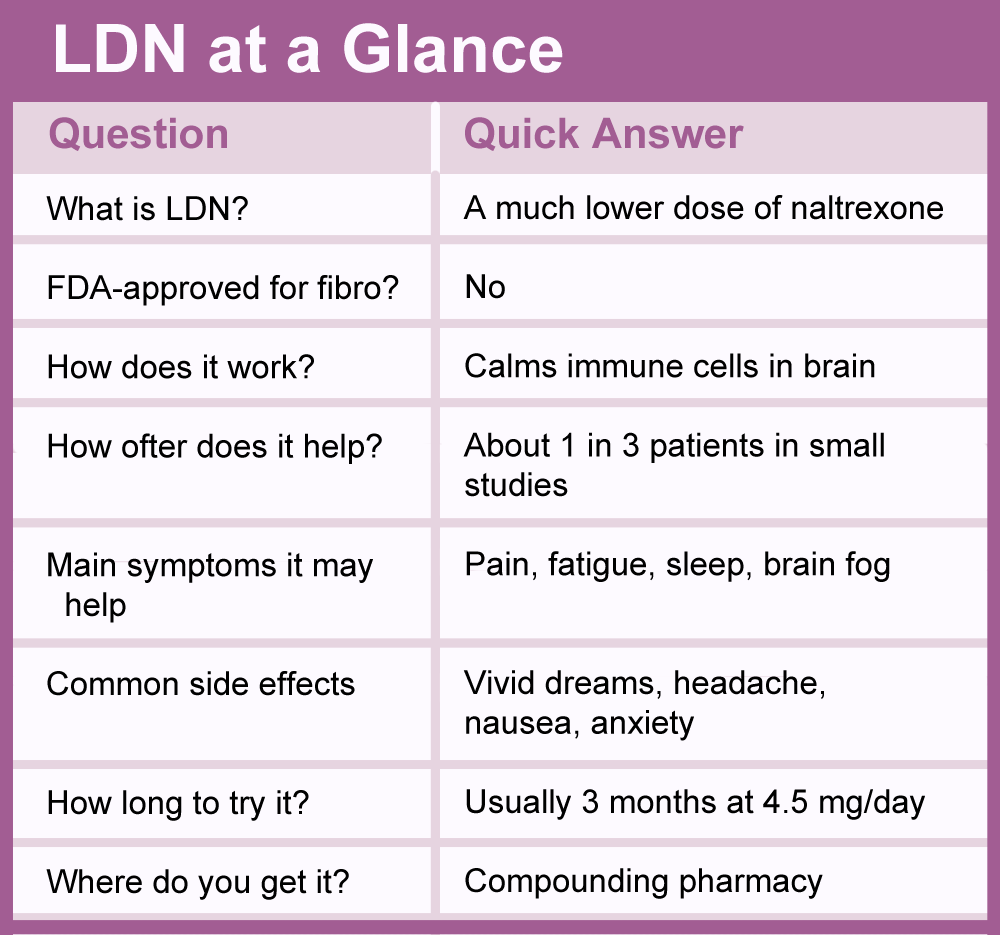
LDN is not FDA-approved for fibromyalgia, and it is not a quick fix. But it is usually well tolerated, its side effects are often mild, and it works differently from the medications most patients are first offered. Instead of targeting nerve cells directly, LDN appears to quiet overactive immune cells in the central nervous system called microglia, which may help turn down the volume on pain, fatigue, poor sleep, and brain fog.
Success Rate
What are the odds that LDN will help you? In the AFSA-funded clinical trial, Sean Mackey, M.D., Ph.D., a pain specialist at Stanford University in Palo Alto, CA, helped evaluate LDN for fibromyalgia. The study found roughly one out of three patients achieved at least a 30 percent improvement in pain.1 The drug produced similar benefits in fatigue and sleep.
Although the AFSA trial only involved 30 patients, it was placebo controlled. It compared how patients felt when they were taking the drug versus how they felt when they were taking a placebo sugar pill.
Nicholas Aitcheson, M.D., a rehabilitation and pain specialist in Queensland, Australia, says, “Around 200 patients have tried LDN for fibromyalgia in our chronic pain clinic. Anecdotally, one-third reaped significant positive results in pain reduction and improved function.” Reports from other pain clinics have found similar results.
Getting LDN Made for You
LDN may work as well as, or possibly better than, some medications used for fibromyalgia. The catch is access. Most local pharmacies stock naltrexone only as a 50 mg tablet. LDN requires a much smaller dose, so a compounding pharmacy must prepare it for you.
Insurance usually does not cover compounded LDN. “Even so, the cost is often modest. Some pharmacies charge as little as 64 cents per day.”
“Some patients and physicians are nervous when using a medication that needs to be compounded,” says Aitcheson. To ease those concerns, he adds, “Naltrexone has been used safely for at least 40 years.” He also points out that LDN uses less than one-tenth of the standard naltrexone dose.
Using a compounding pharmacy adds a few extra steps. Anne Marie McKenzie-Brown, M.D., a pain specialist at Emory University in Atlanta, GA, explains the process in our companion article on Compounding Pharmacies.

Dosing LDN for Fibromyalgia
The most common dose of LDN is 4.5 mg/day, but the range is from 1.5 to 9 mg.2 One dose does not work for everyone. Most fibromyalgia patients take LDN at night, so any side effects are less likely to affect morning function.
“I just recommend that patients start at 4.5 mg LDN at night,” says Mackey. “I don’t think that there is anything magical about that dose.” The fibromyalgia trial used 4.5 mg, and many patients end up near that dose.
If LDN causes vivid or colorful dreams, Fishman recommends taking it in the morning instead. Other side effects may include headache, nausea, or anxiety. These symptoms are usually mild and uncommon. If they persist, your doctor may lower the dose to 3 mg.

Drug-sensitive patients may need a slower start. Aitcheson begins with 1.5 mg per day for one week. He increases the dose to 3 mg the second week. By the third week, he moves patients to 4.5 mg per day. During this phase, he prescribes 1.5 mg compounded capsules.
McKenzie-Brown uses a similar schedule. She often starts patients with half of a scored 3 mg tablet for one to two weeks. If they tolerate it, they increase to 3 mg and later to 4.5 mg if needed. Some patients stay at 3 mg because it provides enough relief.
Be Patient
Low-dose naltrexone does not work quickly. In the fibromyalgia trial, patients took about a month to notice improvement. Aitcheson and McKenzie-Brown both recommend staying on 4.5 mg per day for three months before you give up on LDN.
McKenzie-Brown published a study on LDN use in her chronic pain clinic.3 She found that 12 percent of patients did not get pain relief until after three months. In other words, some patients need more time than they expect.
“I ask patients to reserve judgement on LDN efficacy until the end of three months,” says McKenzie-Brown. “Many patients have told me that they would have stopped LDN, but they are glad they did not.”
Want more treatment guidance like this? Join AFSA’s free email newsletter for patient-friendly updates on fibromyalgia research and treatment options.
Waiting for LDN to Work
While you give LDN time to work, your doctor may also recommend nonopioid medications, physical therapy, aquatic therapy, or other approaches that support symptom relief.
Increasing the Dose
If LDN reduces your symptoms, you may wonder if a higher dose would help. Mackey says he handles this decision “on a case-by-case basis” because “there aren’t any guidelines to direct us in this phase.”
“For the vast majority of people,” says Aitcheson, “going above 6-8 mg per day is not likely to be worth it.” Trying a higher dose requires a new prescription, so talk it over with your physician at a follow-up visit.
LDN and Opioids
Naltrexone blocks opioid receptors, so patients often ask whether they must avoid opioids while taking LDN. The answer depends on the dose, timing, and how often you use the opioid.

If you take an opioid only on bad days, your doctor may still consider LDN. Some patients take the opioid during the day and LDN at night. “Patients may not notice any difference in the opioid’s effectiveness,” says Mackey. “Or they may experience a reduced benefit of the opioid due to the LDN.”
If you take tramadol (a weak opioid) or another opioid, Fishman may still recommend LDN. But he starts patients on a lower dose of 1 mg per day and increases 0.5 mg per week until the 4.5 mg dose is reached.
Patients who take opioids around the clock need extra caution. In these cases, Fishman may start with very low-dose naltrexone, at 0.5 mg or less. Aitcheson adds that patients on opioids should expect more gastrointestinal side effects during the first few weeks of LDN.
“In this era of the opioid epidemic where opioids were prescribed when all else failed for chronic pain,” says Fishman, “we need to consider positioning alternative strategies early on, including LDN.”4
Keep Fibromyalgia Research Moving
AFSA helped put LDN on the fibromyalgia research map, and we have funded eight projects in in the past two years. Your gift helps fund more fibromyalgia treatment studies.
Learn your LDN compounding options and costs.
Symptoms | Medications | Alternative Therapies | Muscle Pain Relief | Fibro Friendly Exercises
LDN for Fibromyalgia References
If your doctor is hesitant to prescribe LDN for your fibromyalgia, here’s a great article: Aitcheson N, et al. Aust J Gen Pract. 2023. Low-dose naltrexone in the treatment of fibromyalgia: A systematic review and narrative synthesis 52(4):189-195. Free Report
- Younger J, Mackey S, et al. Arthritis Rheum 65(2):529-538, 2013. Report (free to read)
- Bruun-Plesner K, et al. Pain Med 21(10):2253-61, 2020. Report
- McKenzie-Brown AM, et al. J Pain Res 16:1993-1998, 2023. Free Report
- Kim PS, Fishman MA. Curr Pain Headache Rep 24:64, 2020. Abstract